Sunday, 3 October 2021


DIABETIC KETOACIDOSIS WITH DENOVO DETECTED DM WITH VIRAL PYREXIA UNDER EVALUATION


HELLO GUYS, This is an online e log book to discuss our patient de-identified health data shared after taking his/her/guardians signed informed consent.

Here we discuss our individual patients problems through series of inputs from available global online community of experts with an aim to solve those patients clinical problem with collective current best evidence based input

I've been given this case to solve in an attempt to understand the topic of "patient clinical data analysis" to develop my competency in reading and comprehending clinical data including history, clinical findings, investigations and come up with diagnosis and treatment plan.

UNIT 5 ADMISSION: 

A 21year old male resident of miryalaguda came to the casualty with

Chief complaints:-

Fever since 5 days, decreased appetite since 7days, vomiting  since 1day, sob since morning.

History of presenting illness:-

Patient was apparently asymptomatic 5days back then he developed fever which is of incidious in onset, intermittent and is of high  grade fever,a/w chills and relieved on medication.  Pt has H/o  1episode of vomiting 1day back which is non bilious,non projectile.

No h/o any burning micturition,throat pain,cold,cough.


PAST HISTORY:-

Not a k/c/o HTN,DM, CAD, asthma, TB, epilepsy.


PERSONAL HISTORY:-

Patient has mixed diet with normal appetite and adequate sleep. 

he has normal bowel movements and bladder filling. 

No addictions. 


No significant family history or allergic history. 


GENERAL EXAMNATION:-

Patient is c/c/c with moderate built and moderate nourishment. 

No pallor, icterus, cyanosis, clubbing, lymphadenopathy, pedal edema. 

VITALS:

BP: 140/90 MMHG, 

PR: 120bpm 

Temp: 98.2°F, 

RR: 40 CPM, 

SPO2: 99% 

Systemic examination:-

RS: BAE+,NVBS

CVS: S1 ans S2 heard. No murmurs. 

P/A: soft and non-tender. 

CNS: No focal deformities. 


INVESTIGATIONS:-

1) HEMOGRAM : 

Hb: 8.2

TLC: 15800

N:89

L:6

PCV: 30

Mcv:63.7

MCH:17.4

MCHC:27.3

PLC:3.37

RBC:4.71


2) LFT:

3)CUE

4)RBS:194 
5)BLOOD UREA:29
6)SERUM CREATININE:0.8 

7)URINE FOR KETONE BODIES:

8)ABG@2PM 


9)SERUM ELECTROLYTES @2pm
S.ELECTROLYTES@ 10PM 


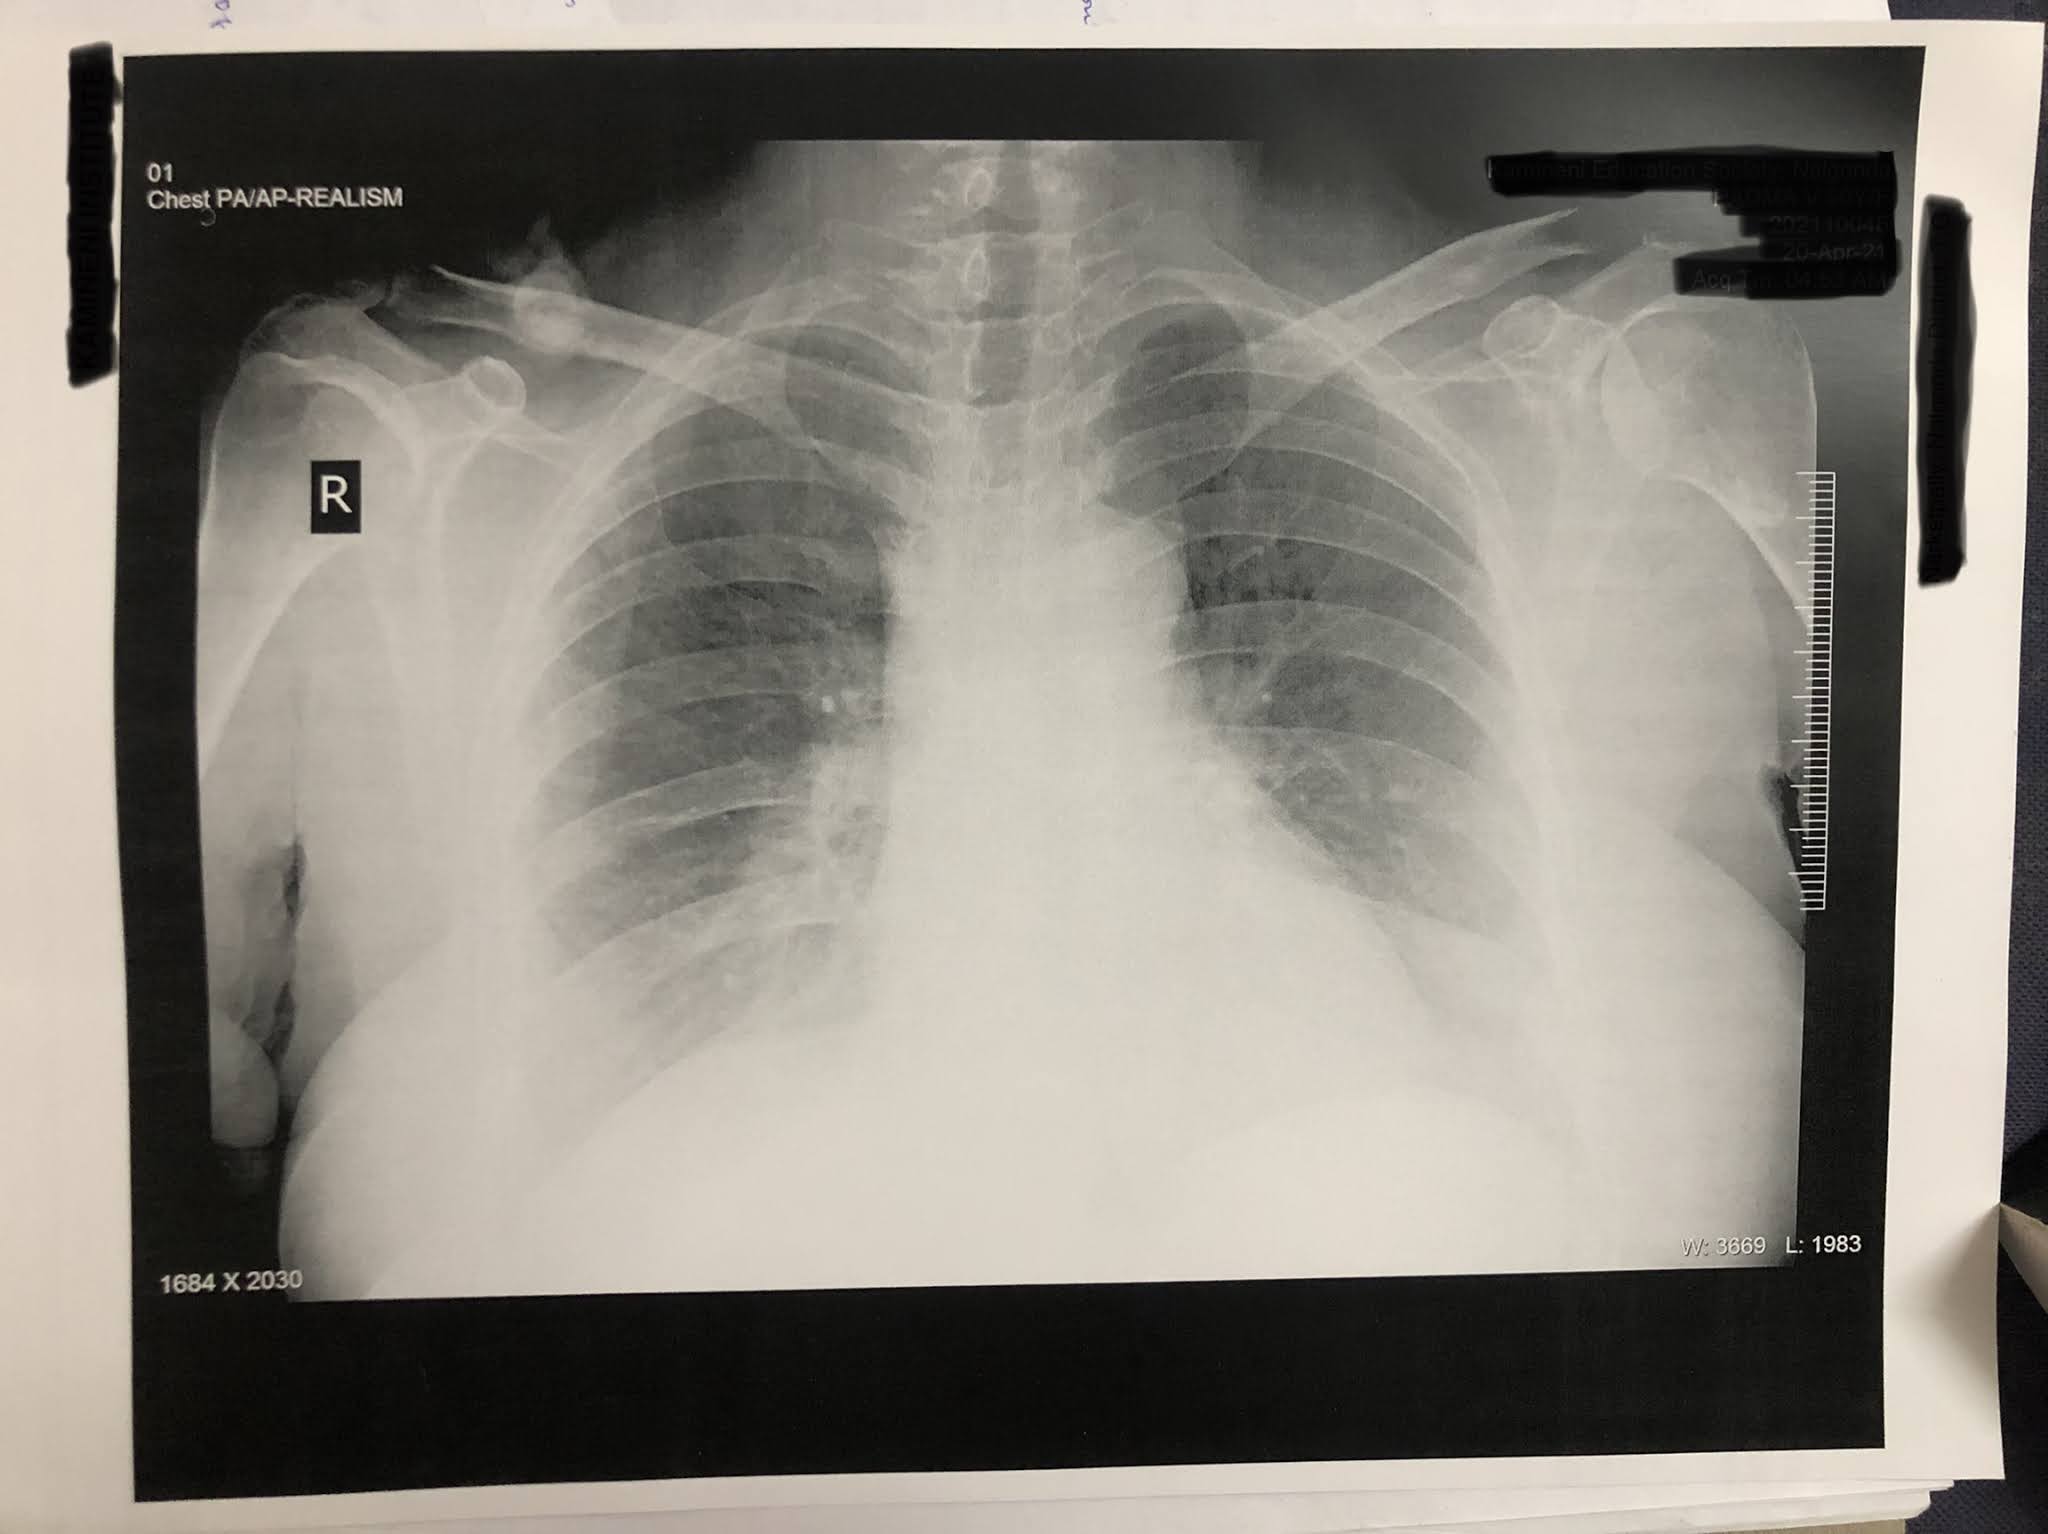
10) Chest xray PA view: 


PROVISIONAL DIAGNOSIS:DIABETIC KETOACIDOSIS WITH DENOVO DETECTED DIABETES MELLITUS WITH VIRAL PYREXIA UNDER EVALUATION

TREATMENT: 
On DAY-1
1)NBM till further orders
2)IVF 3lit NS  @500ml/hr(in 3hrs) f/by IVF NS@250ml/hr 
3)Inj. HAI 4IU IV/stat f/b Inj. HAI 1ml (40IU) in 49ml NS @ 4ml/hr(untill ABG correction)
4)Inj. PAN 40mg IV/OD
5)IVF 5%DEXTROSE @50-100ml/hr(when GRBS <150) [increase/decrease acc. to GRBS]
6)Inj.OPTINEURON 1amp in 100ml NS/IV/OD 
7)GRBS monitoring hourly
8) Strict i/o. Monitoring
9)Inj. KCl 2amp in 500ml NS @100ml/hr

On DAY-2 :
SOAP NOTES:

S: 
No fever spikes,sob decreased ,no fresh complaints
O:
BP-110/90mm hg
PR-74bpm
CVS:S1S2 heard
Rs:BAE +,NVBS
P/A:soft
A:
HAGMA, DKA
Hemogram:
ABG @1AM

@8AM
@3PM

S.ELECTROLYTES:@8AM
@5PM
@10.30PM


P:
1)IVF 0.45% NaCl,RL @100ml/hr 
2)Inj. KCl 2amp in 500ml NS @100ml/hr
3)Inj. HAI 1ml (40IU) in 39ml NS @ 4ml/hr(untill correction of acidosis)
4)Inj. PAN 40mg IV/OD
5)Inj.OPTINEURON 1amp in 100ml NS/IV/OD 
6)GRBS monitoring hourly
7)Strict i/o. Monitoring
8)NBM till further orders


DAY-3 :
S: Patient sob decreased,No fresh complaints

O: BP 110/80 mm hg
PR: 70 bpm
CVS: s1 s2 heard 
RS: BAE+ NVBS 
P/A: soft 

S.ELECTROLYTES @8AM


Assesmemt : over night patient grbs around 290 mg/dl and Patient anion gap is reducing day by day and subjectively feeling better .

Plan : Look for today morning abg and stop iv insulin infusion and start him on NPH and HAI


Monday, 26 April 2021

1601006131 SHORT CASE

 This is an online E log book to discuss our patient’s de-identified data shared after taking his/her/guardian’s signed informed consent”


MBBS FINAL SHORT CASE

—————————————————————————

35 year old male patient, resident of ramchandrapuram, works as a daily wage labourer, a chronic smoker (1 pack of beedi every 2 days) and a chronic alcoholic (90ml daily) since 20 years presented with a 3 month history of painless papules with erythema that started initially over the face then gradually extended to upper limb, low limbs and trunk 

  • No hypodense lesions 
  • No fever 
  • No pus
  • No loss of sensations
  • No genital lesions 

Patient got over the counter  topical cream, soap and some oral drugs from nearby medical shop 

He used them for 2 months, few lesions regressed but few persisted on nose, ear lobe, hands, legs and trunk.

14 days ago patient developed blackish skin discolouration over hands and feet with skin peeling, cracking, ulcer formation associated with burning sensation and erythema all over the body.

Since 4 days patient developed continuous high grade fever associated with chills and rigors.

Associated with Loss of appetite 

There is no history of similar complaints in the past 

EXAMINATION:

  • Face: loss of eyebrows, thickened earlobe
  • Oral cavity: dark erythematous lesions on the palate
  • Multiple lesions of different sizes with ill defined erythematous borders and pale hypopigmented centre with peeling and raw areas are seen on trunk, limbs and face
  • Scaly hyperpigmented plaques with fissures noted involving the feet Extending  from the sole to the dorsal aspect of the foot
DIAGNOSIS:

Hansen’s disease 


1601006131 LONG CASE

 This is an online E log book to discuss our patient’s de-identified data shared after taking his/her/guardian’s signed informed consent.”


FINAL EXAM LONG CASE

————————————————————————————

A 50 year old female patient a resident of Nalgonda, home maker came to the OPD with chief complaints of pain and stiffness in several joints since 1 year.

History of present illness:

She was apparently asymptomatic 10 years ago, then she developed a dull aching type of pain and stiffness in her finger joints(MCP joints) of right hand with limitations of movements at the joints. 

Then within 6 months of onset the disease progressed to involve other joints of the right hand and left hand as well(wrist joint and elbow joint) 

Within 4 years of onset she started feeling pain in the joints of the feet and ankle joint. 

Since 3 months the pain became unbearable limiting  her activities

The pain was insidious in onset, slowly progressive dull aching type of pain, non radiating, associated with swelling, stiffness and limitations of movements in the involved joints.

Stiffness and pain was more in the first 1 hour of waking up and gradually improved on movement.

There are few exacerbations associated with fever.

  • No deformities 
  • No loss of weight.
  • No involvement of distal interphalangeal joint
  • No butterfly rash
  • No abnormal jerky movements (chorea)

PAST HISTORY:

She has no similar complaints 10 years ago. 

No history of thyroid, Asthma, hypertension, diabetes 

DRUG HISTORY

No known drug allergies 

MENSTRUAL HISTORY:

  • Menarch: 13 years 
  • Regular 29 day cycles 
  • Menopause: 47 years 

Family history:

No similar complaints

Personal history : 

  1. Diet: mixed 
  2. Appetite: normal 
  3. Bowel and bladder: regular 
  4. Sleep: adequate 
  5. No addictions 

General examination: 

patient is conscious coherent and cooperative 

Moderately built and nourished 

  • No edema
  • No icterus 
  • No cyanosis 
  • No lymphadenopathy 
  • No pallor 

VITALS:

  1. Temperature: a febrile 
  2. Blood pressure: 115/70
  3. Respiratory rate: 15 CYCLES/MIN
  4. Pulse rate: 76bpm

LOCAL EXAMINATION:

INSPECTION 

Skin : 

No pigmentation 

No scars 

No atrophic changes 

Nails: normal 

Soft tissues: swelling over the joints 

Deformities : no deformities 


PALPATION

Skin: warm

Sensations are preserved 

Soft tissues: no edema 

Joint capsule: mild swelling over the joint 

Tenderness over the joint (squeeze test)

Movements: 

Decreased range of movements at PIP, MCP, wrist, elbow, ankle joints 

All active and passive movements at the involved joints and painful.


EXTRA ARTICULAR MANIFESTATIONS:

Eye: no ocular manifestations (episcleritis, scleritis, keratoconjuctivitis sicca)

Ear: no hearing loss

Muscle: no muscle atrophy 

GIT: no xerostomia, no parotid gland enlargement, no dysphasia 

No lymphadenopathy 


SYSTEMIC EXAMINATION 

CARDIOVASCULAR SYSTEM

Apex beat: 5th intercostal space lateral to midclavicular line 

S1 and s2 heard 

JVP normal

Pedal edema: absent 


RESPIRATORY SYSTEM

Breath sounds: normal 

No additional breath sounds 


CENTRAL NERVOUS SYSTEM

cranial nerves intact 

Reflexes preserved

Sensations preserved 

Joint position sense: intact 

ABDOMEN

No abnormal findings found

DIFFERENTIAL DIAGNOSIS

1. Osteoarthritis 

2. Rheumatoid arthritis 

INVESTIGATIONS:

1. Complete blood picture 

2. ESR 

3. CRP

4. Rheumatoid factor 

5. Liver function tests 

6. Renal function tests 

7. Urine examination 

8. Antibodies 

9. X-ray 


X ray Findings: 
1. Decreased joint space 
2.osteoporosis 
3. Mild erosions 


Rheumatoid factor: strongly positive 
Anti CCP antibodies: negative


C-Reactive protein: positive 

ESR: Elevated


PROVISIONAL DIAGNOSIS:

                 RHEUMATOID ARTHRITIS 


TREATMENT:
1. Methyl prednisolone 
2. Hydrocortisone 
3. Tramadol hydrochloride